
x
Facing a diagnosis of prostatic adenocarcinoma, you may be weighing active surveillance against surgery or radiation while worrying about costs and sexual or urinary side effects. This guide helps you understand who qualifies for monitoring alone, what treatment choices mean, and how to anticipate insurance and drug expenses.
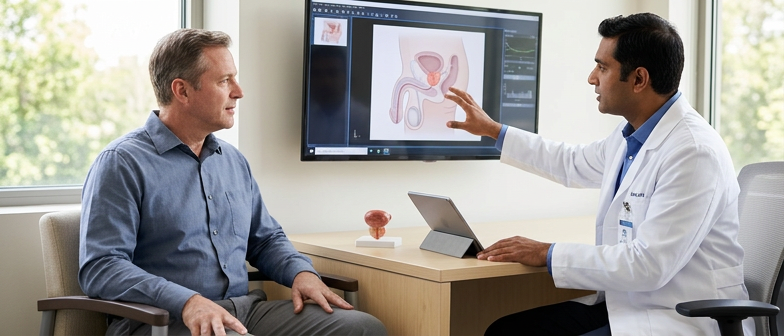
Prostatic adenocarcinoma is the most common type of prostate cancer, starting in the gland cells that produce seminal fluid. These cells line small glands and ducts in the prostate and can acquire genetic changes that let them grow without normal control. Early on, the abnormal cells stay inside the prostate, but more aggressive tumors can invade nearby tissues or spread to lymph nodes and bones. Age is the strongest risk factor, and family history, inherited gene changes, and race or ethnicity also affect risk. Hormones such as testosterone influence how these tumors grow, which is why many treatments aim to lower or block hormonal signals.
Many cases of prostatic adenocarcinoma grow slowly and may never cause symptoms or shorten life. Pathologists and doctors use the Gleason score or Grade Group, PSA levels, and imaging tests to estimate how likely a tumor is to grow or spread. Low‑grade, small‑volume cancers limited to the prostate often behave indolently, so careful active surveillance or watchful monitoring can be appropriate, while higher‑risk disease usually needs prompt treatment. Recognizing this wide range, from very slow to clearly aggressive tumors, helps prepare for later decisions about close monitoring, surgery, radiation, or combining local treatment with systemic therapy.
For men with low‑risk or very slow‑growing prostatic adenocarcinoma, a common question is whether they are good candidates for active surveillance instead of immediate treatment. Active surveillance is a structured plan for cancer that is small, confined to the prostate, not causing symptoms, and usually linked with a low PSA level and low Gleason score. The aim is to delay or avoid surgery or radiation while closely tracking the disease through regular PSA tests, digital rectal exams, imaging, and sometimes repeat biopsies. If these tests suggest the cancer is becoming more aggressive, treatment can begin while the disease is still highly curable.
Both active surveillance and watchful waiting delay treatment, but they differ in intensity and in goals. When people compare watchful waiting versus active surveillance, active surveillance focuses on preserving the chance of cure, using scheduled testing and clear triggers for switching to surgery, radiation, or other therapies. Watchful waiting involves more relaxed follow‑up, usually without repeated biopsies, and the goal is to control symptoms if they arise rather than to cure the cancer. This may be chosen when life expectancy is limited, other serious illnesses are present, or the cancer is unlikely to shorten a person’s life.
Who qualifies for prostate cancer watchful waiting is usually different from those offered active surveillance. Watchful waiting is often reserved for older men or those with significant heart, lung, or other medical problems, when side effects of curative treatment could be more harmful than the cancer itself. In this setting, doctors and patients agree to focus on comfort and symptom relief, using hormone therapy or pain control only if prostatic adenocarcinoma causes problems. Active surveillance is typically recommended for healthier men who could tolerate treatment later but wish to avoid immediate side effects such as urinary leakage or sexual changes while keeping careful observation of their cancer.
| Approach | Monitoring Intensity | Primary Goal | Best Suited For | When To Be Cautious |
|---|---|---|---|---|
| Active surveillance | High, structured tests | Preserve chance of cure | Younger, healthier, low‑risk cancer | Unreliable with poor follow‑up access |
| Watchful waiting | Low, symptom‑driven | Relieve or prevent symptoms | Older adults, serious other illnesses | Less ideal if long life expectancy |
| Active surveillance | Regular PSA, exams, imaging | Delay surgery or radiation | Those worried about side effects now | If anxiety about untreated cancer is high |
| Watchful waiting | Occasional visits, fewer tests | Avoid burdensome procedures | Those prioritizing comfort care | If cancer already causing bothersome symptoms |
If you are wondering whether you qualify for active surveillance for Prostatic Adenocarcinoma, your team looks at both the tumor and your overall health. This approach is usually for very low‑ or low‑risk cancer, with a relatively low PSA, a Gleason score of 6 or sometimes 3+4, and tests showing the cancer is confined to the prostate and growing slowly. Age, other illnesses, and life expectancy help doctors judge whether they can safely delay treatment side effects while still keeping a chance for cure.
To choose between watchful waiting and active surveillance, think about your goals and how closely you want to be monitored. Watchful waiting is often used when life expectancy is limited and focuses on treating symptoms if they appear. Active surveillance instead uses regular PSA tests, exams, imaging, and repeat biopsies, with a clear plan to move to surgery or radiation if the cancer progresses. Discuss with your urologist which option best fits your values and daily life.
For localized prostatic adenocarcinoma, the most common definitive treatments are radical prostatectomy and radiation therapy. Surgery removes the prostate and is done by a urologic surgeon, while radiation is delivered by a radiation oncologist either from outside the body or through radioactive seeds. Both approaches can often control or cure the cancer but differ in recovery, side effects, and how insurance treats prostate cancer surgery versus radiation costs. Some health plans cover hospital-based surgery and office-based radiation differently, so reviewing deductibles, copays, and out-of-pocket limits with your insurer or a financial counselor helps you understand your likely personal expenses before choosing a treatment.
Side effects should be discussed before treatment. Many people want specific questions ready for their doctor about sexual changes, including erections, orgasm, and ejaculation after surgery or radiation. Your urologist, radiation oncologist, or primary care clinician can review options such as medicines, devices, pelvic floor therapy, or counseling to help maintain or regain intimacy. Asking in advance what changes to expect, how long they might last, and what support is offered can help you and your partner decide what feels right for you.
Urinary and bowel symptoms differ between treatments. Incontinence after prostate removal is usually managed first by your urologist, often with pelvic floor exercises and, when needed, referral to a pelvic health physical therapist or later surgical implants. Radiation can irritate the rectum and bowel, so new rectal pain or bleeding after prostate radiation should prompt a call to your radiation oncologist or treatment center, which may involve a gastroenterologist. Knowing who treats incontinence, bowel issues, and pain helps you get timely care and reduces anxiety during and after treatment.
Before treatment for prostatic adenocarcinoma, ask how surgery, radiation, or hormone therapy could affect erections, desire, and future fertility. Ask whether nerve‑sparing surgery is possible, what options exist if you have erection problems, when it is safe to resume sex, and which urologist or sexual health specialist to contact if new difficulties appear.
If you may have your prostate removed, ask your surgeon about your personal risk of incontinence, how long leakage may last, and which pelvic floor exercises or other strategies you should use before and after treatment. Ask clearly who treats incontinence after prostate removal in your system, what symptoms count as urgent, and exactly how to reach the right clinician if they occur.
When you are diagnosed with prostatic adenocarcinoma, a key step is estimating your prostate cancer treatment out-of-pocket costs. Your spending depends on your plan’s deductible, co-pays, coinsurance, and annual maximum, plus whether your doctors and hospitals are in-network. Surgery and radiation may be covered differently. A prostatectomy often creates one large bill around your hospital stay, while radiation treatments are broken into many sessions, spreading charges across several months. Before choosing between surgery and radiation, ask the billing office or a financial counselor for written estimates and confirm how each option is covered by your insurance.
Drug coverage also strongly affects your budget, especially if you need long-term hormone therapy or newer prostate cancer medicines. When you compare prescription plans for prostate cancer drugs, review the formulary to see if your medications are listed, what tier they are in, and whether prior authorization or step therapy is required. Then look at the monthly premium, any pharmacy deductible, and the co-pay or coinsurance for the drugs your doctor expects you to use. Ask how costs change in any coverage gaps and whether mail-order pharmacies lower prices. Bringing a list of current and likely future prescriptions to a benefits counselor can help you choose a plan that fits your treatment and finances.
Am I a good candidate for active surveillance for prostatic adenocarcinoma?
You may be eligible if the cancer is small, confined to the prostate, PSA is low, and the Gleason score is 6 or sometimes 3+4. Age, other illnesses, and life expectancy also matter, so your urologist and oncologist should review your full case.
How is watchful waiting different from active surveillance in prostate cancer?
Active surveillance uses a set schedule of PSA tests, exams, imaging, and repeat biopsies, with curative treatment if the cancer progresses. Watchful waiting is much less intensive and usually for men with shorter life expectancy, focusing on comfort and symptom relief.
How can I estimate my out-of-pocket costs for prostate cancer surgery and radiation?
Call your insurer and a hospital financial counselor for written estimates. Ask how deductibles, copays, and coinsurance will apply, which surgeons and radiation centers are in-network, and how many separate bills you might get for surgery, hospitalization, and each radiation session.
What sexual and urinary side effects should I ask about before prostate cancer treatment?
Ask about risks of erectile dysfunction, loss of ejaculation, lower libido, and urinary incontinence. Discuss whether nerve-sparing surgery is possible, what treatments exist for erections or leakage, and which specialist to see if new sexual or urinary problems appear later.
Who should I contact if I have rectal pain after prostate radiation?
First call your radiation oncology team, as they know your treatment and common late effects. If pain is severe, or there is bleeding or fever and you cannot reach them, go to urgent care or an emergency department and bring your radiation records.