
x
Many older adults want sturdier, more natural‑feeling teeth than traditional dentures. This guide explains how dental implants for seniors are assessed and planned, including bone and gum health, imaging, medications, risks, options for multiple missing teeth, and ways to manage treatment costs.
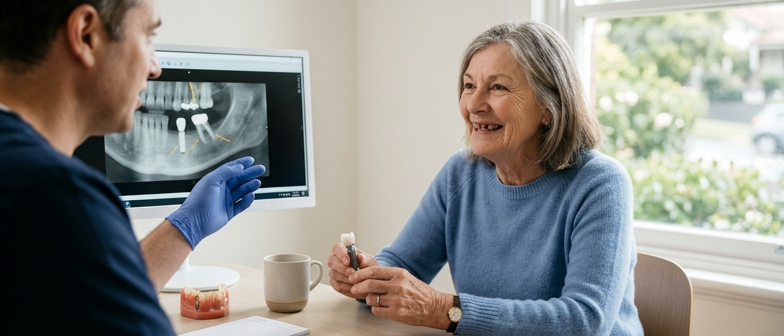
Dental implants are small posts placed in the jaw to support replacement teeth, designed to look and function more like natural teeth than removable dentures. Older adults may consider them when dentures feel loose, cause gum soreness, or make chewing and speaking difficult. Implants can replace one or several missing teeth and may offer a more fixed, stable option than full or partial dentures. In later life, the choice to use implants usually involves balancing comfort, chewing ability, and confidence with healing capacity, cost, and overall health.
For seniors, goals often include stronger biting, enjoying a wider range of foods, and less worry about dentures slipping, but age adds extra considerations. Bone quality, gum condition, medications, and illnesses such as diabetes or osteoporosis affect whether implants are suitable and how they are planned. There are specific risks, including slower healing, infection, or reduced implant stability when bone or gums are compromised, so these factors are assessed rather than assuming the same result for everyone. Dentists or specialists generally explain realistic outcomes for replacing several missing teeth or switching from dentures to implant supported teeth, helping people weigh potential benefits against limitations before deciding.
Planning dental implants for seniors begins with a thorough clinical assessment rather than using age as the main deciding factor. The dentist reviews medical and medication history, including heart disease, diabetes, osteoporosis, and any blood-thinning or bone‑modifying drugs, because these can affect healing and complication risk. Smoking, risk of falls, and general mobility are considered as they influence surgery and long‑term cleaning of the implants. An oral examination assesses gum health, any active gum disease, the amount and quality of available bone, and how existing dentures or remaining teeth function together. When the case is complex or involves restoring several missing teeth, a referral to a prosthodontist or another implant‑focused clinician may be recommended to plan bite, appearance, and long‑term function in more detail.
Imaging is central to planning for older adults. Standard dental x‑rays are often combined with a cone beam CT scan, which gives a three‑dimensional view of the jaws. This CBCT scan helps the dentist judge bone volume and density and see how close nerves and sinuses are to proposed implant sites, guiding decisions about bone grafting or other preparatory procedures. When choosing an implant dentist, many seniors consider easy access to the clinic, experience with older patients, and clear discussion of potential risks. These may include infection, delayed healing, nerve disturbance, sinus problems in the upper jaw, and a greater chance of implant failure if chronic conditions or oral hygiene are not well controlled. A structured planning visit aims to balance these risks against expected improvements in function and comfort so the person can make an informed choice.
| Assessment Item | Why It Matters For Seniors | Typical Discussion Outcome | Suggested Action Level |
|---|---|---|---|
| Medical conditions and medications | Influence healing and implant complication risk | Clarify diabetes, heart disease, osteoporosis and drug use | High priority review |
| Mobility, falls risk and smoking | Affect surgery safety and long‑term cleaning ability | Discuss support at home and smoking changes | Risk‑focused planning |
| Gum health and existing dentures | Impact infection risk and implant stability | Identify gum disease and denture fit issues | Treat or stabilise before implants |
| CBCT scan and other imaging | Shows bone volume, density and nearby structures | Decide if extra imaging will change the plan | Selective use, not routine |
| Complex bite and appearance needs | Full‑arch or multiple implants need detailed design | Consider prosthodontist dental implant referral | Specialist‑led planning |
| Understanding dental implant risks for seniors | Supports informed consent and realistic expectations | Review infection, healing delay, nerve and sinus issues | Shared decision‑making |
For seniors considering dental implants, cone beam CT imaging may be used when standard X-rays do not show jaw bone quality, nerve position, or sinus anatomy clearly. Clinical guidance recommends ordering CBCT only when the extra detail is likely to change the implant plan, particularly in situations with bone loss, past extractions, or complex replacement of several teeth, because radiation exposure is higher than with routine dental imaging.
When implant treatment is complex, such as full mouth rehabilitation, medically complicated cases, or concerns about bite and appearance, a general dentist may suggest referral to a prosthodontist or another dental specialist. The prosthodontist focuses on planning and restoring implants to suit existing teeth, jaw function, and long-term maintenance, and may coordinate with the patient’s doctor when medicines or general health could influence healing.
For seniors considering dental implants, the amount and quality of jawbone strongly influence whether treatment is suitable and how it heals. Bone loss from long‑term missing teeth, gum disease or denture wear can leave bone too thin or soft to hold an implant. In these cases, a bone graft may be recommended first to rebuild volume and support. Grafting can use processed bone material, sometimes with a membrane, and usually needs a healing period before implant placement. Health history, including osteoporosis and other conditions that affect bone metabolism, is considered when planning surgery and estimating recovery.
Gum and soft‑tissue health are equally important because they help protect the bone and the implant from bacteria. Active gum disease raises the risk of infection around implants and further bone loss, so it is generally treated first with professional cleaning and tailored home care. Dry mouth or reduced manual dexterity, which are common in older adults and may relate to medication use, can make plaque control harder and should be discussed before treatment. Once gum inflammation is under control, implant procedures can be planned, with regular maintenance visits to monitor for early signs of problems and to adapt cleaning techniques over time.
Medications that influence bone turnover, including some osteoporosis drugs, form a key part of risk assessment. In certain situations they have been linked to delayed healing or rare jawbone complications after invasive dental procedures. Because of this, the dentist will usually review medical notes, may liaise with the prescribing doctor and can adjust the surgical approach, timing and follow‑up. Careful imaging and conservative techniques are used to reduce risks. By looking at bone quantity, bone quality, gum status and overall medical health together, seniors receive a clearer picture of realistic implant options and likely healing times.
For seniors, the amount and quality of jawbone strongly influence dental implant planning. Bone can shrink after extractions, long‑term dentures or gum disease, leaving limited support for an implant. If scans show inadequate bone, the dentist may recommend a graft using donor material or bone from the mouth, followed by a healing period before surgery. These extra procedures are considered when discussing overall risks, recovery and whether fixed teeth are worth the added treatment steps.
Medicines commonly prescribed in older age, especially osteoporosis drugs such as bisphosphonates or denosumab, also affect implant decisions. A small number of patients on these therapies experience delayed healing or jaw problems after invasive dental work. The dental team therefore reviews medical history carefully and may consult the doctor before surgery. The plan can be adjusted by changing implant sites, staging procedures or in some cases favouring non‑surgical options to balance safety and long‑term outcomes.
For seniors with several missing teeth or who rely on full or partial dentures, implant‑based solutions aim to improve chewing and confidence compared with removable plates. Options include implant‑supported bridges, where a small number of implants hold a row of replacement teeth, and implant‑retained overdentures, which clip onto implants but can be removed for cleaning. Some people prefer fixed full‑arch restorations anchored on multiple implants, which feel more like natural teeth but usually involve more planning, appointments and cost. The most suitable design depends on how many teeth are missing, bone quality, general health, and preferences around stability, cleaning and budget, so treatment plans are typically individualised after assessment.
Older denture wearers and those with a history of gum disease need careful evaluation before moving to implants. Long‑term denture use can reduce bone volume, and past periodontal problems may increase the chance of infection around implants, so clinicians normally focus first on improving gum health and checking bone support. This can involve gum treatment, updated home cleaning routines or bone grafting when loss is marked. Medical conditions, medications and the person’s ability to keep the mouth clean are considered because they influence healing and long‑term outcomes. Clear discussion of expected benefits, risks, treatment steps, timeframes and non‑implant alternatives helps seniors decide whether changing from dentures to implant‑supported teeth suits their situation.
Are dental implants suitable for seniors compared with traditional dentures?
Suitability depends on health, bone and gum condition, and medications. Implants can feel more stable than dentures, but need surgery, healing time, and good cleaning ability.
Why might a dentist order a CBCT scan before placing implants in an older adult?
CBCT is used when regular X‑rays do not clearly show bone quality, sinuses or nerves. It helps plan implant position more safely, especially in complex or bone‑loss cases.
What should seniors know about dental implant risks and common complications?
Risks include infection, failed integration with bone, nerve or sinus issues, and peri‑implant gum disease. Conditions such as diabetes, smoking or blood thinners can increase these risks.
Can multiple missing teeth or full dentures be replaced with implant‑based options?
Yes. Choices include implant‑supported bridges, removable overdentures that clip onto implants, and fixed full‑arch restorations. The best option depends on bone levels, health and budget.
How do bone grafts and osteoporosis medication affect implant treatment in seniors?
Bone grafts may be needed when jawbone is thin or shrunk. People on some osteoporosis drugs require careful assessment because these medicines can alter bone healing and complication risk.